Alzheimer’s disease and Parkinson’s disease are both progressive disorders in which brain cells gradually become damaged, but they do not usually begin in the same way. Alzheimer’s disease primarily affects memory and other thinking abilities, while Parkinson’s disease is best known for problems with movement, such as slowness, stiffness and tremor. However, the differences are not absolute: Parkinson’s can cause cognitive problems, while people with advanced Alzheimer’s can develop movement difficulties. The diseases also involve different patterns of abnormal proteins in the brain, although Alzheimer’s- and Parkinson’s-related changes can sometimes occur together.
| Feature | Alzheimer’s disease (AD) | Parkinson’s disease (PD) |
|---|---|---|
| Disease type | Progressive neurodegenerative disorder and the most common cause of dementia | Progressive neurodegenerative movement disorder; cognitive impairment can develop as the disease progresses |
| Main system initially affected | Brain networks involved in memory and cognition, particularly the hippocampal/entorhinal regions early in the disease | Motor circuits, particularly pathways involving dopamine-producing neurons in the substantia nigra |
| Typical first prominent problem | Memory impairment, especially difficulty learning or recalling recently acquired information | Movement impairment, particularly bradykinesia, rigidity and/or resting tremor |
| Dominant clinical feature | Progressive impairment of memory, thinking, language, reasoning and daily functioning | Progressive impairment of movement, including slowness, rigidity, tremor, gait and postural control |
| Memory | Usually an early and prominent feature | Can occur, but prominent memory impairment is generally not the defining early feature |
| Thinking and executive function | Problems with reasoning, judgment, problem-solving and orientation become increasingly prominent | Executive dysfunction, slowed thinking and attention problems may occur |
| Language | Word-finding and communication difficulties can become prominent as disease progresses | Speech may become soft, slow or monotonous, particularly as motor symptoms progress |
| Personality / behaviour | Changes in behavior and personality can occur, particularly as disease advances | Depression, apathy and other non-motor symptoms are common; behavioral changes can occur, especially with cognitive impairment |
| Movement symptoms | Usually not the defining early feature; motor impairment can occur in advanced disease | Core feature: bradykinesia, rigidity, resting tremor, gait and postural problems |
| Resting tremor | Not characteristic | Characteristic, although not every person with PD develops tremor |
| Bradykinesia (slowness of movement) | Not a typical defining feature | Core motor feature |
| Balance/gait problems | Can develop later | Common, particularly as PD progresses |
| Sleep abnormalities | Sleep disturbance is common | Sleep problems are common; REM sleep behavior disorder can precede motor symptoms in some people |
| Autonomic symptoms | Can occur, particularly in advanced disease | Relatively prominent; may include constipation, orthostatic hypotension and urinary/sexual dysfunction |
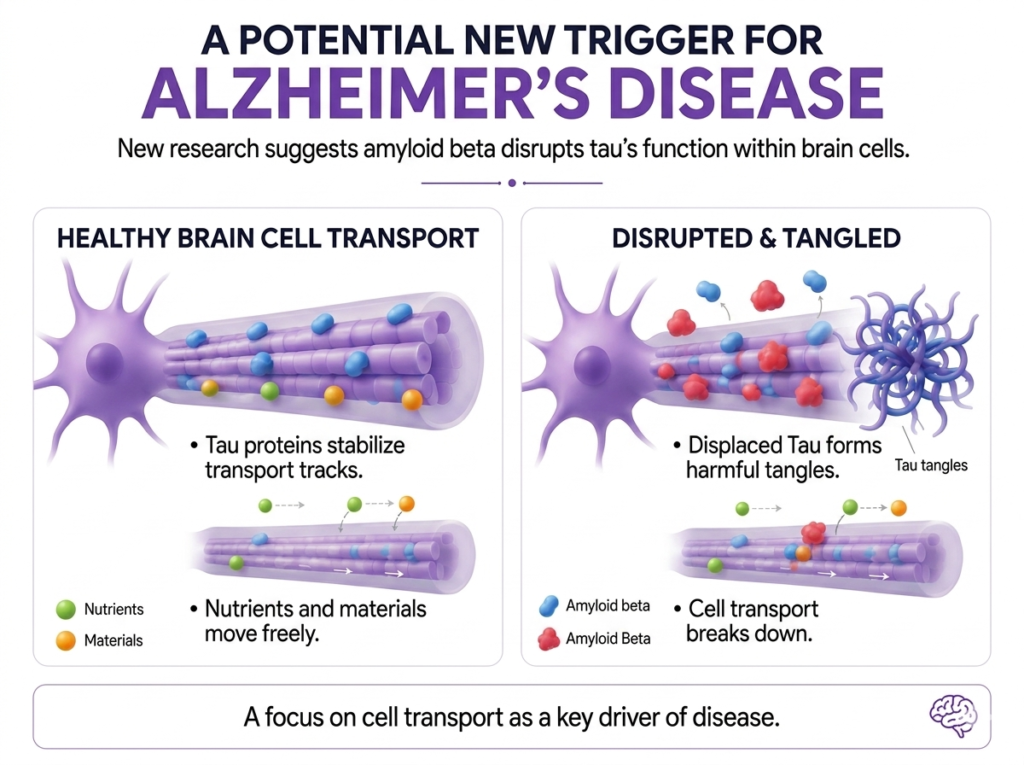
| Primary pathological proteins | β-amyloid plaques and abnormal tau neurofibrillary tangles | α-synuclein-containing Lewy bodies and Lewy neurites |
| Major neurotransmitter/system involved | Multiple neurotransmitter systems become affected; cholinergic dysfunction is particularly relevant to cognitive symptoms | Dopaminergic dysfunction is central to the motor syndrome; other neurotransmitter systems are also affected |
| Characteristic brain changes | Early damage involves the hippocampus and entorhinal cortex, followed by wider cortical involvement and brain atrophy | Degeneration of substantia nigra dopaminergic neurons and dysfunction of basal-ganglia motor circuits |
| Dementia | Central feature of the disease, although the earliest stage may begin with mild cognitive impairment rather than dementia | Dementia can develop, but typically occurs after established Parkinsonian motor disease in Parkinson’s disease dementia |
| Diagnosis | Clinical assessment plus cognitive testing, brain imaging and, increasingly, amyloid/tau biomarkers in blood, CSF or PET | Primarily clinical neurological assessment; imaging helps exclude other disorders. α-synuclein biomarkers are an evolving diagnostic tool |
| Main symptomatic treatment approach | Cognitive symptoms may be treated with cholinesterase inhibitors; memantine may be used in moderate-to-severe disease | Levodopa and other dopaminergic therapies are central to treatment of motor symptoms |
| Overall clinical emphasis | Cognition → memory, reasoning, language and eventually daily function | Movement → bradykinesia, rigidity, tremor and gait/postural problems, followed by possible cognitive decline |
Frequently Asked Questions (FAQs)
1. Are Alzheimer’s and Parkinson’s the same disease?
No. They are different neurodegenerative diseases. Alzheimer’s mainly affects memory and thinking, while Parkinson’s mainly affects movement. However, some symptoms and underlying brain changes can overlap.
2. Can Parkinson’s disease cause memory problems?
Yes. Some people with Parkinson’s develop problems with attention, thinking and memory. When significant dementia develops after established Parkinson’s disease, it is called Parkinson’s disease dementia.
3. Does Alzheimer’s disease cause tremors?
Tremor is not a typical early symptom of Alzheimer’s disease. Movement problems can occur in advanced disease, but a prominent resting tremor is much more characteristic of Parkinson’s disease.
4. What is the main difference in the brain?
Alzheimer’s disease is strongly associated with beta-amyloid plaques and tau tangles, while Parkinson’s disease is associated with abnormal alpha-synuclein deposits called Lewy bodies.
5. Can someone have both Alzheimer’s and Parkinson’s-related brain changes?
Yes. The two types of pathology can occur together. This is one reason why symptoms of neurodegenerative diseases can sometimes overlap and why diagnosis may require more than looking at a single symptom.
6. Can Alzheimer’s disease and Parkinson’s disease occur together?
Yes. Mixed neurodegenerative pathology is relatively common in older adults.
References
Nussbaum RL, Ellis CE. Alzheimer’s disease and Parkinson’s disease. N Engl J Med. 2003;348(14):1356-64. doi:10.1056/NEJM2003ra020003.
American Brain Foundation. Disease connections: Alzheimer’s and Parkinson’s [Internet]. [cited 2026 Sep 21].
National Institute on Aging. How biomarkers help diagnose dementia [Internet]. Bethesda (MD): National Institutes of Health; [cited 2026 Sep 21].
National Institute of Neurological Disorders and Stroke. Parkinson’s disease [Internet]. Bethesda (MD): National Institutes of Health; [cited 2026 Sep 21].
Hansen D, Ling H, Lashley T, Holton JL, Warner TT. Review: Clinical, neuropathological and genetic features of Lewy body dementias. Neuropathol Appl Neurobiol. 2019;45(7):635-654. doi:10.1111/nan.12554.
Walker Z, Possin KL, Boeve BF, Aarsland D. Lewy body dementias: Dementia with Lewy bodies and Parkinson disease dementia. Mayo Clin Proc. 2015;90(7):869-876. doi:10.1016/j.mayocp.2015.04.006.